

If you’ve just been told you might need ACDF surgery, this article is for you. You may have a disc herniation in your neck, or bone spurs pressing on a nerve root, or both. You’ve probably been dealing with arm pain, numbness into your fingers, or weakness in your grip for weeks or months. Take a breath. This article explains what ACDF is, what the procedure involves, and what questions are worth sitting with before you make a decision.
ACDF stands for anterior cervical discectomy and fusion. It removes a damaged disc in your neck through a small incision in the front, then fuses the two vertebrae around that disc space. It’s one of the most commonly performed spine surgeries in the United States, with a strong track record for relieving arm pain and hand numbness caused by cervical nerve compression.
What is ACDF and what conditions lead to it?
ACDF is done when a disc in the cervical spine (your neck) is pressing on a nerve root or the spinal cord. The disc sits between two vertebrae and acts as a cushion. When it herniates, ruptures, or degenerates enough to narrow the space where nerves pass through, the result is often radiculopathy. Radiculopathy is nerve pain that travels from the neck down through the shoulder and arm, sometimes reaching the hand. It can come with tingling, numbness, or weakness in the hand or fingers. The pattern of where the symptoms go tells your doctor which level is involved. The most commonly affected levels are C5-C6 and C6-C7. For patients near West Hempstead dealing with persistent neck and arm symptoms, neck pain care from a spine specialist starts with identifying which nerve root is involved before discussing any procedure.
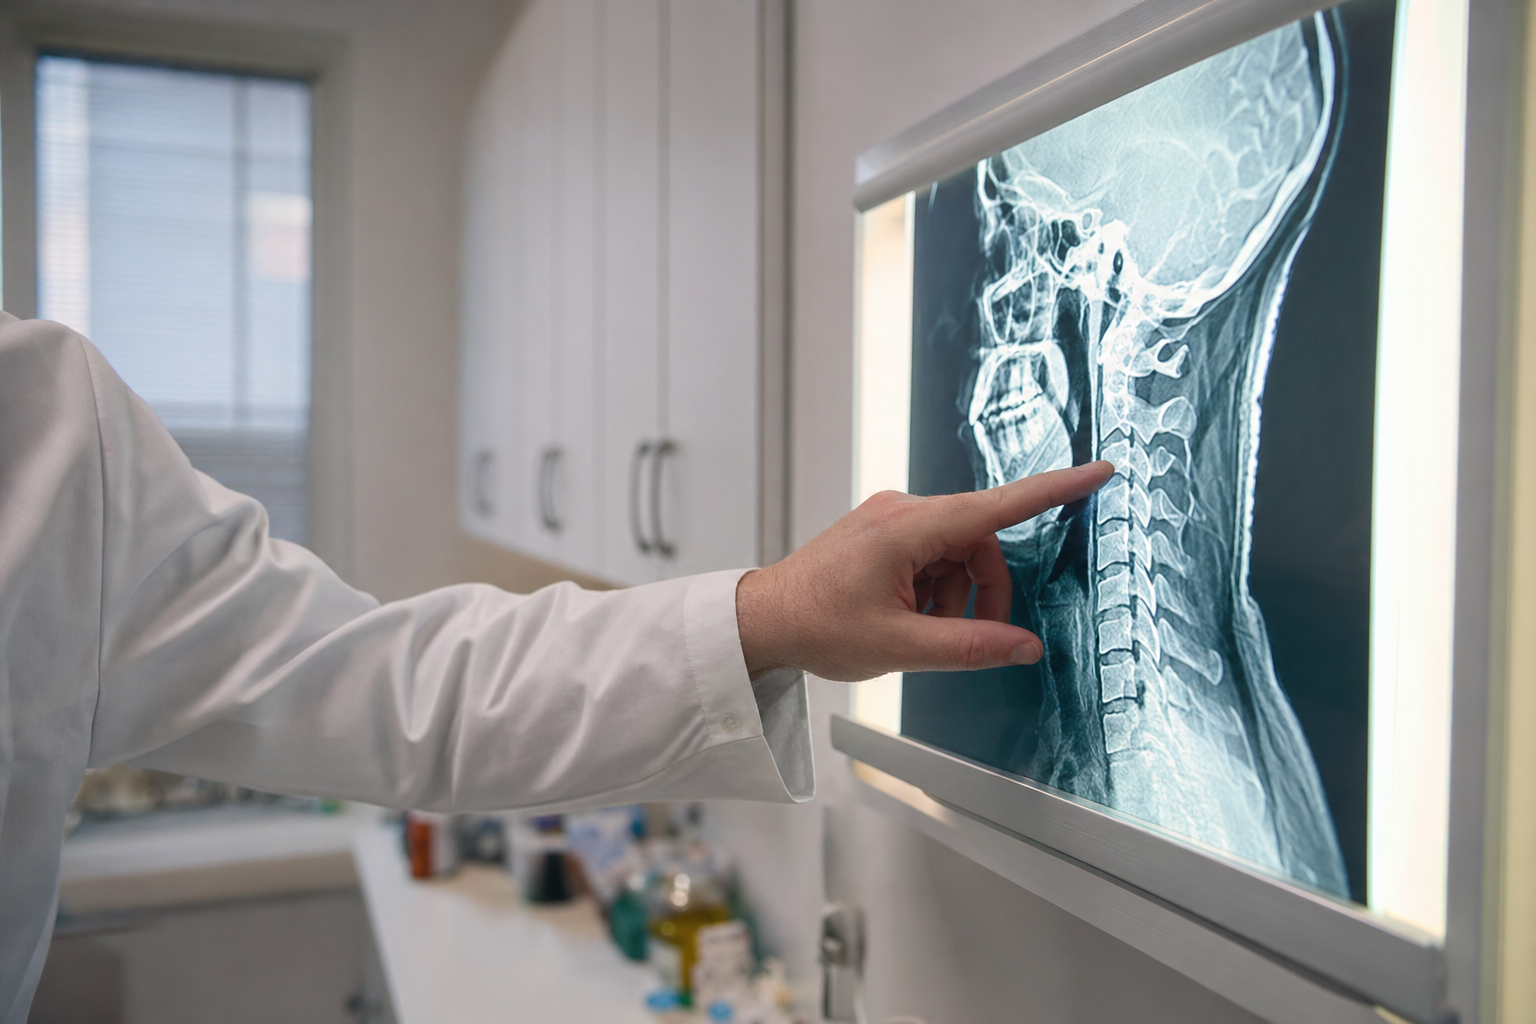
What’s happening in your cervical spine
Cervical disc disease happens when one or more of the discs in your neck change shape, lose fluid, or develop small tears. That can cause the disc to bulge or herniate into the space where nerves exit the spinal canal. For some people it happens from a single injury. For most, it’s a gradual process that accelerates in the 40s and 50s. Bone spurs can also form around a degenerated disc and narrow the same openings. An MRI shows the disc, the nerves, and the degree of compression. But the imaging doesn’t tell the whole story. Pain that’s clearly following a nerve pattern, with matching neurological findings on physical exam, carries more weight in the decision than what a scan shows alone.
What the surgery actually involves
The ‘anterior’ in ACDF means the surgeon approaches from the front of the neck, not the back. A small horizontal incision, often less than two inches, is made near the midline. The surgeon moves the trachea and esophagus aside to reach the spine directly. The damaged disc is removed. The surgeon then places a bone graft or an implant in the disc space to restore height and allow fusion. A small titanium plate and screws hold the two vertebrae in position while fusion takes place over 3 to 6 months. The whole operation typically takes one to two hours. Many patients go home the same day or after one overnight stay.
Recovery: the first weeks and months
Most patients notice significant improvement in arm pain within the first days to weeks after surgery, as the nerve decompresses. Back-of-the-neck soreness from the surgical approach takes longer. A soft cervical collar may be recommended for a few weeks, depending on your surgeon’s preference. Driving is usually off the table for a few weeks while the collar is on. Physical therapy is commonly added at the 4 to 6 week mark, focusing on range of motion and the muscles supporting your neck. Fusion takes 3 to 6 months to be visible on imaging, and some patients take closer to a year for full solid fusion. Most people return to desk work within 2 to 4 weeks and to physical labor in 6 to 12 weeks, again depending on their specific job.
| Stage | What most patients experience |
|---|---|
| Days 1 to 7 | Arm pain often improves quickly; neck soreness from surgical incision |
| Weeks 2 to 6 | Soft collar phase if required; light daily activities return; driving typically off |
| Weeks 6 to 12 | PT begins; return to desk work for most; sustained loading still limited |
| Months 3 to 6 | Fusion progressing; most patients return to full activity |
| Month 6 and beyond | Fusion confirmed on imaging; full clearance for most activities |

What ACDF changes, and what it doesn’t
ACDF eliminates motion at the fused segment. For most patients, losing movement at one or two cervical levels has little functional impact. The remaining neck levels compensate. There’s some evidence that adjacent disc disease can develop over time as neighboring levels absorb more movement. That risk is real but often overstated. Surgery success is measured by whether the nerve symptoms resolve, not by how much neck mobility looks the same on paper. Most patients with the right diagnosis get significant or full relief from arm pain and numbness. Neck pain itself can be more variable. If your main complaint is chronic neck pain without clear nerve involvement, the evidence for ACDF is less consistent.
The decision: when ACDF makes sense
The decision for ACDF typically involves: documented nerve compression on MRI at the level matching your symptoms, neurological findings on exam (weakness, reflex changes), and an adequate trial of conservative treatment that hasn’t worked. ‘Adequate trial’ usually means 6 to 12 weeks of physical therapy and, often, an epidural steroid injection. If you’re dealing with progressive weakness, hand coordination loss, or myelopathy (spinal cord compression with balance problems), the timeline for surgery may be shorter. Talk to your own physician about the specifics of your case. The team at the West Hempstead spine center evaluates cervical spine cases across the full range, from conservative treatment through to surgery, so you can get a complete picture before deciding. This article is general information, not a substitute for your own workup.
- Confirmed nerve compression on MRI matching your symptom pattern
- Neurological findings on physical exam (weakness, reflex changes, sensory loss)
- Trial of conservative treatment (PT, medication, possibly a steroid injection) without sufficient improvement
- Symptoms severe enough to affect daily function or quality of life
- For myelopathy (spinal cord involvement): earlier surgical discussion is typically recommended